
Diabetic Neuropathy: Pain Relief Alone Won’t Prevent Foot Ulcers
The best treatment for diabetic neuropathy in the feet is personalised and multimodal: tight glycaemic and risk-factor control, a guideline first-line medicine if pain needs it, topical options where appropriate, and protective footwear with daily foot checks to prevent ulcers. The goal is meaningful pain relief and ulcer prevention, not a cure. Any open wound, spreading redness, or swelling needs urgent medical attention.
TL;DR:
- First line medicines bring moderate relief to only one in four to one in three people, so assess response after about 12 weeks.
- Older adults and people with reduced kidney function need lower starting doses and closer monitoring because gabapentin and pregabalin can accumulate as clearance declines.
- For pain confined to small areas or when oral medicines cause problems, lidocaine plasters or topical capsaicin can limit whole body side effects.
- Check both feet daily, avoid walking barefoot, and arrange podiatry visits every three to six months for people with prior ulcers, sensory loss, or deformity.
- Any open sore, spreading redness, warmth, or swelling warrants urgent medical attention, even when reduced sensation prevents pain from signaling infection.
Table of Contents
- What is diabetic peripheral neuropathy in the feet?
- Principles of treating neuropathy in the feet
- Oral medications: first-line options and practical notes
- Topical treatments and local therapies for foot pain
- Non-drug approaches: exercise, therapy, and footwear
- Daily foot care and preventing ulcers
- Red flags: when to see a GP, podiatrist, or specialist urgently
- Types of diabetic neuropathy that affect the feet
- How diabetic neuropathy in the feet is diagnosed
- Realistic timelines for treatment and symptom relief
- Emerging and advanced treatment options on the horizon
- Why footwear deserves more attention in neuropathy care
- Supporting your feet with the right footwear choice
- FAQ
- Sources
What is diabetic peripheral neuropathy in the feet?
Diabetic peripheral neuropathy typically develops as a distal symmetrical pattern, meaning it starts in the toes and spreads upward, affecting both feet in a mirror-image way. Small nerve fibre damage tends to cause burning, tingling, or stabbing pain, while large fibre involvement brings numbness, poor balance, and loss of vibration sense.
A significant complication is that many people lose protective sensation in their feet without feeling any pain at all. This silent loss is dangerous because a blister, cut, or pressure sore can go unnoticed until it becomes infected or ulcerated. Risk rises with long-standing or poorly controlled blood glucose, obesity, high blood pressure, and abnormal cholesterol levels. Because nerve damage and reduced sensation often progress together, foot checks matter just as much as pain management, sometimes more.
Principles of treating neuropathy in the feet
Guideline-based care for painful diabetic neuropathy rests on three pillars that work together rather than in isolation.
- Optimise the underlying drivers: glucose control, blood pressure, lipids, and weight management can slow nerve damage progression.
- Consider pathogenetic therapies where evidence supports them: options such as alpha-lipoic acid target the metabolic processes behind nerve injury.
- Manage pain symptomatically: first-line oral medicines, topical agents, and non-drug approaches reduce discomfort and improve function.
Clinical groups such as NeuPSIG classify treatments into first, second, and third lines based on trial evidence and safety, recommending that the choice be personalised according to a person’s other health conditions, medicines, and tolerance for side effects. Older adults and those with reduced kidney function need lower starting doses and closer monitoring, since several common neuropathy medicines are cleared through the kidneys and can accumulate to unsafe levels.
Oral medications: first-line options and practical notes
Three drug classes dominate first-line recommendations for painful diabetic neuropathy: serotonin-noradrenaline reuptake inhibitors (SNRIs) such as duloxetine, tricyclic antidepressants (TCAs) such as amitriptyline, and gabapentinoids such as pregabalin and gabapentin. Randomised trials and meta-analyses support all three classes, though the NeuPSIG overview notes that average benefits across trials are modest, and no single drug works for everyone.
Practical prescribing points include:
- Start low, go slow: doses usually begin small and increase gradually over several weeks to balance pain relief against side effects.
- Adjust for kidney function and age: pregabalin and gabapentin require dose reduction in people with impaired renal clearance and in frail older adults.
- Expect common side effects: drowsiness, dizziness, dry mouth, and weight gain are frequent with these medicines and often ease with time or dose adjustment.
- Give treatment a fair trial: most guidelines suggest assessing effectiveness after around 12 weeks at an adequate dose before switching or adding another agent.
One in three to one in four people treated with these first-line agents in trials achieve at least moderate pain relief, which is why guidelines frame success as meaningful improvement rather than complete resolution, according to the NeuPSIG summary. Combination therapy, pairing a gabapentinoid with an SNRI or TCA at lower individual doses, is sometimes used under specialist supervision when a single agent gives insufficient relief, though this requires careful monitoring for additive side effects.
Topical treatments and local therapies for foot pain
Topical and local treatments suit people with pain localised to the feet, older adults who are more sensitive to oral drug side effects, and anyone already taking several medicines for other conditions. Because these treatments act at the skin rather than throughout the body, they tend to cause fewer systemic side effects.
- Capsaicin 8% patch: applied in a clinical setting, this patch has been approved for painful diabetic peripheral neuropathy after trial evidence showed effective pain reduction with fewer central nervous system side effects than oral medicines, as detailed in a review of painful diabetic neuropathy treatment.
- Capsaicin cream: a lower-strength, self-applied version that some people use daily, though a warming or burning sensation on first use is common.
- Lidocaine plasters: numb the skin locally and suit people with well-defined areas of burning pain, particularly where oral medicines are poorly tolerated.
For pain that resists these measures, specialist centres may offer neuromodulation. Spinal cord stimulation and repetitive transcranial magnetic stimulation have shown benefit in selected patients with severe, refractory painful diabetic neuropathy, but these approaches require referral to a pain specialist and careful patient selection, as outlined in research on advanced therapies for diabetic foot complications.
Non-drug approaches: exercise, therapy, and footwear
Structured exercise does more than support general health in diabetic neuropathy. Supervised aerobic and resistance training, combined with dietary counselling, has been shown to delay the onset and progression of neuropathy in at-risk individuals and can ease existing symptoms, according to a review of painful diabetic neuropathy treatment. A sensible programme usually combines two to three sessions a week of moderate aerobic activity with balance and strength work, adjusted for any existing foot complications.
Cognitive behavioural therapy (CBT) and pain self-management programmes act as a useful adjunct for people living with chronic neuropathic pain, helping to reduce the distress and disability that often accompany long-term discomfort.
Alpha-lipoic acid (ALA) has meta-analytic evidence for symptomatic benefit, with trials using oral or intravenous regimens around 600 milligrams showing improvement in symptoms and nerve function signs. Regulatory status and availability vary between countries, so expectations should stay modest rather than treating it as a guaranteed fix.
- Exercise: slows progression and improves symptoms with regular, supervised activity.
- CBT: helps manage the psychological burden of chronic pain.
- ALA: offers symptomatic benefit for some, with variable availability.
- Therapeutic footwear: redistributes plantar pressure away from vulnerable areas, reducing ulcer risk for people who have lost protective sensation.
Pro Tip: Pair any new exercise routine with a same-day foot check, since numb feet won’t signal new rubbing or blisters on their own.
Daily foot care and preventing ulcers
Daily habits do more to prevent ulcers than almost any single medicine, because they catch small problems before they become serious ones.
- Inspect both feet daily, using a mirror to check the soles and checking carefully between the toes for cuts, blisters, or colour changes.
- Moisturise dry skin but avoid applying cream between the toes, where excess moisture can encourage fungal infection.
- Never walk barefoot, indoors or outdoors, since numb feet cannot feel sharp objects or hot surfaces.
- Trim nails straight across and leave callus removal to a podiatrist rather than using blades or over-the-counter corn treatments at home.
- Check shoes before putting them on, feeling inside for grit, seams, or linings that could rub, and rotate pairs to avoid repeated pressure on the same spot.
National guidance from the CDC’s foot care advice recommends well-fitted, protective footwear and regular professional review for anyone with diabetes. People at higher risk, those with prior ulcers, significant sensory loss, or foot deformity, typically need podiatry review every three to six months rather than the annual check that suits lower-risk individuals.
Red flags: when to see a GP, podiatrist, or specialist urgently
Certain signs mean a phone call today, not a wait-and-see approach.
- Any open sore or ulcer, however small it looks.
- Spreading redness, warmth, or swelling, which can signal infection even without pain.
- Fever or feeling generally unwell alongside a foot wound.
- A wound that has not improved after four weeks of basic care, which usually warrants referral to a specialist foot or wound clinic.
Persistent, severe pain that has not responded to first and second-line treatments after a reasonable trial is also a valid reason to ask a GP for referral to a pain specialist or neurologist, rather than continuing to escalate the same medicine alone.
Types of diabetic neuropathy that affect the feet
Diabetic neuropathy in the feet rarely shows up as a single, uniform problem. Sensory neuropathy is the most recognised type, causing the burning, tingling, or numbness most people associate with the condition, and it is this sensory loss that drives ulcer risk by masking injury.
Motor neuropathy affects the small muscles of the foot, leading over time to changes in foot shape, such as clawed toes or a high arch, which shift pressure onto new areas of skin that were not built to bear it. These shifts partly explain why ulcers often form in predictable spots, like the ball of the foot or the tips of the toes.
Autonomic neuropathy affects the nerves controlling sweat glands and blood flow in the feet. Reduced sweating leads to dry, cracked skin that is more prone to splitting and infection, while altered blood flow can affect healing speed. Many people experience a mix of all three types simultaneously, which is why assessment typically checks sensory function, muscle strength, and skin condition rather than relying on pain alone to judge severity.

How diabetic neuropathy in the feet is diagnosed
Diagnosis usually starts with a clinical foot examination, checking reflexes, muscle strength, and skin condition, paired with simple sensory tests. A 10-gram monofilament pressed against specific points on the sole checks for loss of protective sensation, while a tuning fork assesses vibration sense, which often fades early in nerve damage.
For more detailed assessment, nerve conduction studies measure how well electrical signals travel along peripheral nerves, helping to confirm the diagnosis and gauge severity, particularly when symptoms are atypical or another cause of nerve damage needs ruling out. Quantitative sensory testing takes this further, measuring thresholds for temperature and vibration sensation under controlled conditions to detect small fibre damage that basic bedside tests can miss.
These tests matter because the combination of results, not any single measure, guides how urgently footwear and foot-care measures should be introduced. Someone with significant sensory loss on monofilament testing, even without pain, needs the same protective footwear and daily inspection routine as someone with severe burning pain, because the ulcer risk comes from lost sensation rather than from discomfort itself.
Realistic timelines for treatment and symptom relief
Patience matters with diabetic neuropathy treatment, because nerve-related pain rarely responds overnight. Most oral medicines need two to four weeks at an adequate dose before any noticeable effect appears, and guidelines generally recommend continuing at the target dose for around 12 weeks before judging whether a drug has worked, as outlined in the NeuPSIG treatment overview.
Topical treatments such as the capsaicin 8% patch can offer relief within days of a single application, with effects sometimes lasting several months before reapplication is needed. Alpha-lipoic acid and exercise-based interventions tend to work on a slower timeline, with symptomatic and nerve function improvements typically building over several months of consistent use.
It helps to set expectations around partial improvement rather than complete elimination of symptoms. A realistic goal is a meaningful reduction in pain intensity and better sleep or daily function, alongside stable or improving sensory testing results over time. Nerve damage that has already occurred does not reliably reverse, which is why prevention of further damage, through glucose control and foot protection, runs alongside any pain treatment rather than as a separate afterthought.

Emerging and advanced treatment options on the horizon
Research into diabetic neuropathy treatment continues to expand beyond the established first and second-line options. Neuromodulation techniques, including spinal cord stimulation, have moved from experimental to specialist clinical use for severe, treatment-resistant pain, with trial evidence supporting benefit in carefully selected patients, as described in research on advanced therapies for diabetic foot complications.
Newer anticonvulsant formulations and refined delivery methods for existing drug classes are under ongoing study, aiming to improve the balance between pain relief and side effects that currently limits some oral treatments. Gene therapy approaches targeting nerve regeneration remain at an early research stage rather than established clinical practice, and anyone considering a novel or experimental treatment should discuss realistic expectations and trial eligibility with a specialist rather than seeking it outside recognised research settings.
For most people, the practical reality in 2026 remains that the established multimodal approach, combining risk-factor control, first-line medicines, topical options, and protective footwear, delivers the most reliable results while newer techniques mature and become more widely available.
Why footwear deserves more attention in neuropathy care
Good footwear does quiet, unglamorous work in neuropathy management: it removes pressure from vulnerable spots before they become problems. A shoe that fits properly and cushions the right areas can reduce the friction and repetitive pressure that often precede ulcers in feet that can no longer send a pain warning. This is why foot-care guidance consistently pairs medical treatment with footwear advice rather than treating them as separate concerns.
Readers wanting more detail on what makes footwear suitable for neuropathy can explore how specific design features reduce plantar pressure and what distinguishes purpose-built neuropathy footwear from standard comfort shoes.
— Panagiotis
Supporting your feet with the right footwear choice
Protective footwear works alongside medical treatment, not instead of it, and getting that choice right makes daily foot checks easier and more effective. We design our footwear around reducing pressure points and supporting comfortable, stable movement throughout the day, which matters most for feet that cannot always signal when something is wrong.
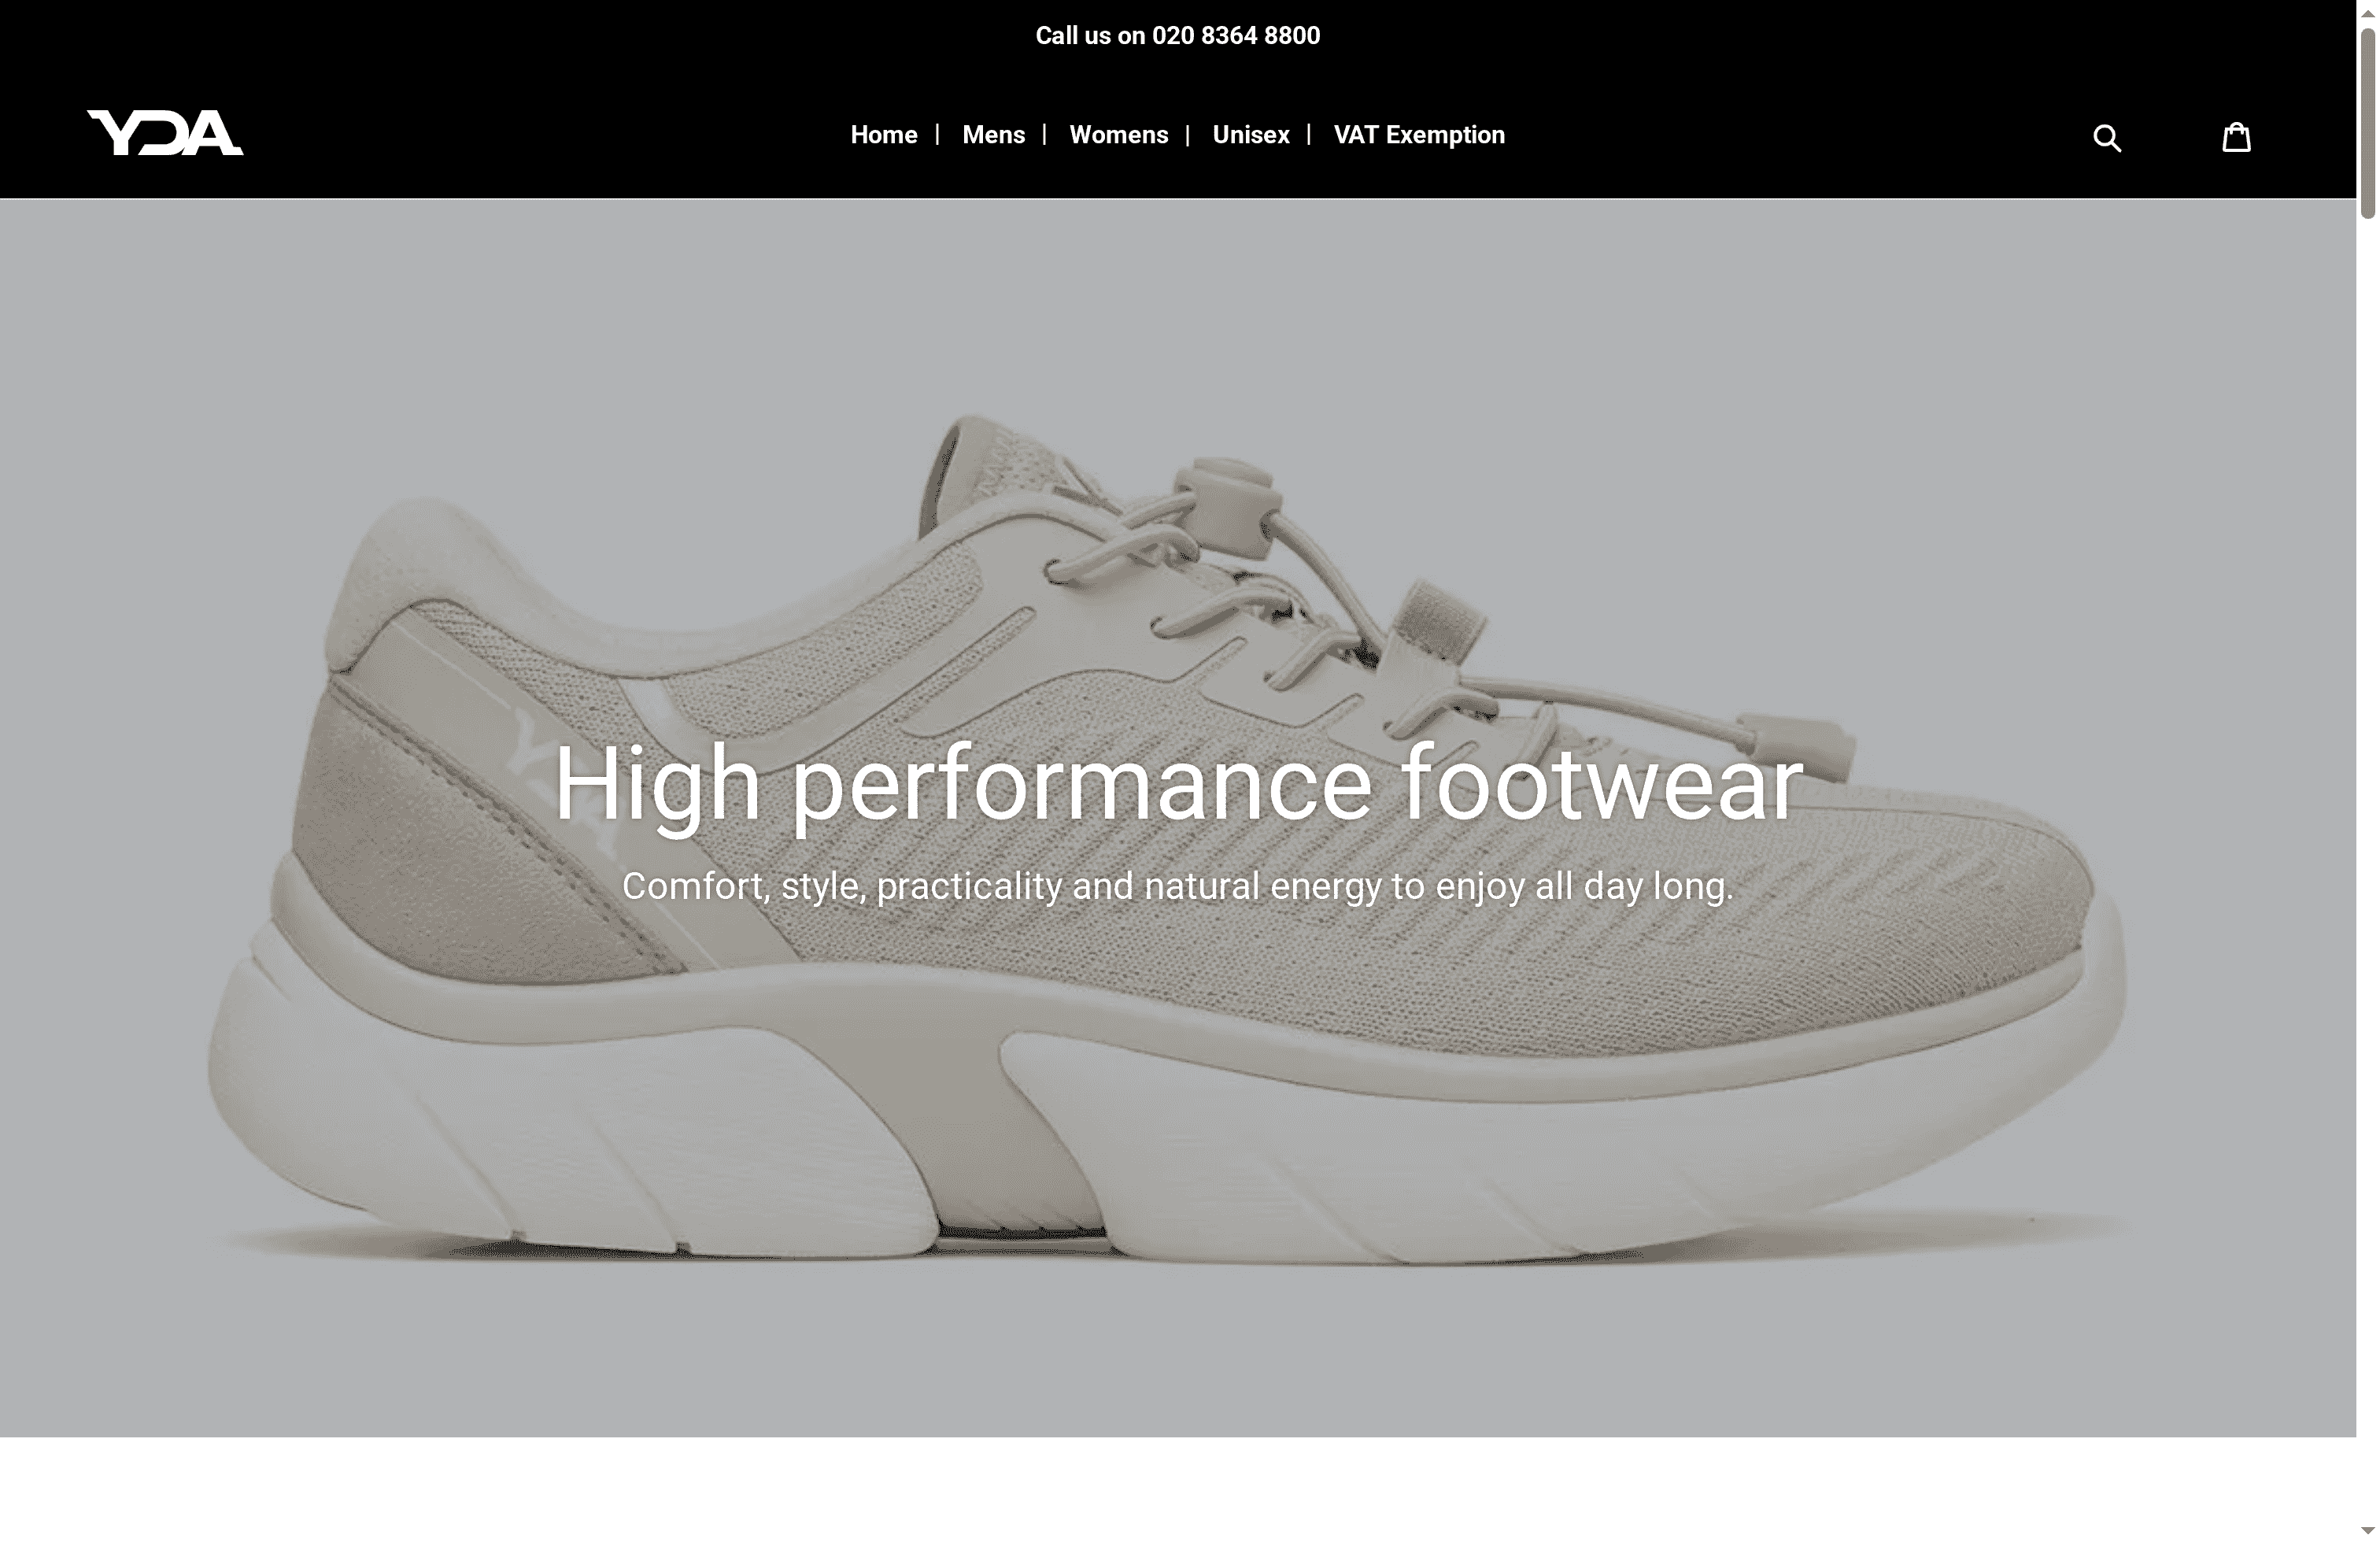
Our high-performance footwear range applies YDA Technology to combine everyday comfort with the kind of structural support that helps distribute pressure more evenly across the foot. If you’re ready to see how the right pair fits into your daily foot-care routine, browse our current range and find the support your feet need today.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
FAQ
Does diabetic foot neuropathy ever go away?
Established nerve damage from diabetic neuropathy does not typically reverse, though symptoms can improve significantly with treatment and better glucose control. Many people achieve meaningful, lasting pain relief even though some degree of numbness or sensory change often remains.
What is the best home treatment for diabetic neuropathy in feet?
At home, the most effective measures are daily foot inspection, wearing well-fitted protective footwear at all times, and keeping blood glucose as stable as possible. Over-the-counter capsaicin cream can help with localised burning pain, but any new or worsening symptoms should prompt a conversation with a GP or podiatrist rather than relying on home treatment alone.
What are three things you should never do to the feet of someone with diabetes?
Never let them walk barefoot, since numb feet cannot feel sharp objects or extreme temperatures. Never cut calluses or corns with blades or apply corrosive corn treatments, since minor nicks can turn into serious wounds. Never ignore a blister, cut, or colour change, however small, since early treatment prevents most ulcers from progressing.
Should you walk a lot with neuropathy?
Regular walking and supervised exercise generally help diabetic neuropathy by supporting circulation and slowing symptom progression, according to reviewed trial evidence. The key is wearing properly fitted, protective footwear and checking the feet afterwards, since people with reduced sensation can develop blisters or pressure sores without noticing during the walk itself.
How long does it take for neuropathy medicines to work?
Most first-line oral medicines need two to four weeks to show initial effect, with guidelines recommending a full trial of around 12 weeks at an adequate dose before assessing whether the medicine is working, based on the NeuPSIG treatment recommendations. Topical treatments such as the capsaicin 8% patch can act faster, sometimes within days of application.
Sources
- An overview of IASP’s Neuropathic Pain Special Interest Group (NeuPSIG) treatment recommendations
- Treatment of painful diabetic neuropathy
- Diabetes and your feet – CDC